



Only 13% of Canadian adults could reach all three core parts of their own health record online in 2025: laboratory and imaging results, immunisation history, and medication history or renewals. 69% could reach at least one of them, according to the Canadian Institute for Health Information.
Those two numbers describe the market better than any forecast. Patients are already online. The records behind them are still scattered across systems that don't talk to each other.
For anyone planning a healthcare SaaS platform, the hard problem is rarely the interface. It's interoperability and tenant isolation, the two constraints that decide whether a product survives its second customer. Get them wrong, and every new clinic, hospital or insurer adds a bespoke integration and a fresh compliance review.
What follows is the build sequence as it unfolds: use cases, expected features, provincial privacy rules, tenant security, architecture models, integration design, and the lifecycle from discovery to launch. It's written for teams preparing a first release in Canada, where provincial variation is normal, and multi-tenancy is the default business model.
Common HealthTech SaaS Use Cases
Every healthtech product idea fits one of six shapes. The shape tells you what data you handle, who signs the contract, and how many other systems must connect before the thing works at all.
| Use case | Main users | Core data | Typical buyer |
|---|---|---|---|
| Patient portal | Patients and families | Results, appointments, messages | Clinics and hospitals |
| Medication management | Patients and pharmacists | Medication history and renewals | Pharmacies and primary care |
| Remote monitoring | Patients and care teams | Device readings and alerts | Health startups and hospitals |
| Multidisciplinary treatment planning | Clinicians and specialists | Imaging, notes and care plans | Hospitals and specialist teams |
| Clinic operations | Front desk and clinicians | Scheduling, encounters and billing | Independent clinics |
| Insurance claims workflow | Claims staff and providers | Claims, eligibility and benefits | Insurers and benefit providers |
Patient portals are the most requested and the least self-contained. Patients want results, appointments and messages in one place, but every one of those views depends on a record system you don't control. The portal is only as good as its read integration.
Medication management serves patients and pharmacists with history and renewals. Small scope, high consequence. A wrong interaction flag costs more trust than a missing dashboard ever will.
Remote monitoring platforms take device readings, raise alerts and route them to a care team. The engineering that matters is escalation, because an unacknowledged reading is worse than no reading. Say a patient's overnight oxygen dips twice; the product needs to know who to wake, in what order, and what happens when nobody answers.
Multidisciplinary treatment planning is where several clinicians review imaging and notes together and agree a plan in one sitting. These apps carry the heaviest data and the smallest user count, and a hospital team usually buys them rather than a procurement department.
Clinic operations software covers scheduling, encounters and billing for independent practices. Deal sizes are modest, volumes are high, and the buyer expects to self-serve in an afternoon. If your roadmap stretches into shared care across conditions such as dementia, compare dementia care coordination tools before you design the data model, since the feature set runs well past a shared calendar.
Insurance claims workflows handle eligibility, claims and benefit checks. The data is financial rather than clinical, but the integration surface is wider than most clinical products face, because provider, plan and member records all have to agree.
Pick one row before you pick a stack. Write down the users, the data sources and the buyer, then note which row your first release matches. If the answer is two rows, cut one.
Essential Features Clinicians and Patients Expect
A useful first release fits the clinic's daily routine. Patients need to book and understand follow-up steps; clinicians need to review records and complete work without hunting through the system.
For patients
Online booking that follows clinic rules: Support appointment types, provider availability, cancellation windows, and room scheduling to prevent double-bookings.
Secure messaging with a clear response time: Set expectations and route messages to a queue that clinic staff can manage.
Results in plain language: Show the result, its reference range, and what the patient can do next, including how to book follow-up when needed.
Reminders on useful channels: A text can remind someone about an appointment, while email can deliver a document.
For clinicians
Structured notes with a fast path: Combine free text with templates that reflect how the local team documents care. A template borrowed from another province may not fit local practice, so build templates around the team's existing workflow.
Task queues instead of crowded inboxes: Group abnormal results, unsigned notes, and pending referrals into lists staff can work through.
Alerts that fire once: Repeated alerts for the same abnormal result can teach clinicians to ignore them.
For administrators
Tenant settings, roles, and user management, with a named owner for each tenant.
Branding and usage reports, so a clinic group can show its board how the product is being adopted.
For the system itself
CSV and FHIR bundle import and export. Clinics need practical ways to bring data in and move it out.
Searchable change history for every record a clinician edits.
Choose the first-release features by how often the pilot clinic will use them. Keep weekly tasks in scope and defer functions that only a large hospital needs. Integration and privacy requirements can shape the work early, so review any feature that handles patient data before development begins.
AI features need a clear review path. In 2024, 7% of surveyed Canadian physicians used artificial intelligence or machine learning in their main practice to support patient care, up from 2% in 2021, according to the Canadian Medical Association and Canada Health Infoway national physician survey. A result summary or triage suggestion should include consent prompts, a named human reviewer, an audit trail, and a way to escalate incorrect output.
Before launch, check three practical points: patients can book on a phone, staff can see who changed a record, and a locum can get access promptly.
Canadian Privacy Rules by Province
Canada is not one regulatory zone. A platform that assumes it is will clear a security review and fail a legal one, because the regime governing a record depends on where it was collected, where it's processed and where it's disclosed.
| Location | Regime that usually applies | Design control to build |
|---|---|---|
| British Columbia, Alberta and Quebec | Substantially similar provincial private-sector law for in-province processing | Regional storage and consent records per tenant |
| Ontario, New Brunswick, Nova Scotia and Newfoundland and Labrador | Substantially similar provincial health-information legislation | Health-data rules set in tenant configuration |
| Interprovincial or cross-border transfer | PIPEDA may apply again | Data-flow map and documented subprocessors |
| Other provinces and territories | Local legislation, confirmed by counsel | Configurable policy set for each tenant |
The federal Personal Information Protection and Electronic Documents Act governs personal information in commercial activity, but substantially similar provincial laws generally apply instead for in-province processing in British Columbia, Alberta and Quebec. Ontario, New Brunswick, Nova Scotia, and Newfoundland and Labrador carry substantially similar health-information legislation of their own, as the Office of the Privacy Commissioner of Canada sets out. That same guidance is plain about the baseline: collection, use and disclosure must be fair, lawful, consented to, and limited to stated, reasonable purposes.
The rules that catch teams out
Three patterns account for most of the privacy rework on a multi-tenant build.
Consent is per purpose, not per user: A patient who agreed to appointment reminders has not agreed to analytics, or an external AI call. Store purpose beside the consent record, not in a policy document nobody opens.
Transfers reopen the question: Moving data between provinces, cloud regions, analytics services or an external AI API can bring PIPEDA back into scope even where a provincial law otherwise applies.
Deletion is a workflow: Retention schedules and deletion requests must run across backups, logs and exports, and someone has to be able to prove it happened.
The build response is a data inventory that names the collection province, processing location, disclosure destination and information type for every field group. Pair it with configurable regional storage, a documented subprocessor list, immutable access logs and separate consent metadata per tenant. Our PIPEDA healthcare compliance guide walks through the consent records in more detail.
Practical rule: if a data flow crosses a provincial border, treat it as a fresh assessment rather than a settings change.
Before the first pilot, three checks: confirm each tenant's province in writing, map every data flow end to end, and get legal review of the result. Encryption and access-control detail belong to the next layer down.
Security Controls That Protect Tenant Data
Tenant isolation is a feature you can test and log, not a promise in a contract. These are the controls auditors ask to see, and the ones that decide whether one clinic can ever see another's patients.

Technical controls
Least-privilege, role-based access, so a receptionist's session can't reach a clinical note.
Encryption in transit and at rest, with keys held outside the tenant's own database.
Tenant identifiers isolated in storage and in every query, not just in the application layer.
Policy checks at each API and database access point, plus immutable access logs.
Data-use controls
Health Canada's guidance on protecting privacy in health data sets out the mechanics: monitor and control access, remove direct identifiers such as names, addresses and health-card numbers when data is used or shared, establish formal agreements governing that use, run privacy assessments, and report and respond to breaches. In product terms, that means analytics environments built on de-identified or pseudonymised datasets, re-identification risk assessed before any sharing, and signed data-use agreements stored alongside the tenant record.
Operational controls
Privacy-impact assessment records, breach detection with named owners, a notification procedure that has been rehearsed, and restore plans tested last quarter. For a wider set of administrative safeguards, Ciphar's guide to healthcare data safeguards covers the process side that code can't enforce.
Consider a clinic administrator in one tenant who opens the patient list. Even with a bug in the application layer, the query returns nothing from the second tenant, because the database policy scopes every read to the tenant identifier in the session rather than the one in the request. That's the difference between isolation and good intentions.
Run this test before each release.
Create two synthetic tenants with deliberately similar names.
Attempt cross-tenant reads and writes through every API and every screen.
Record the logs for each attempt, including the blocked ones.
Fix what failed, then repeat the sequence before the next release.
Test before you trust: if you can't produce a log of a blocked cross-tenant request, you don't have isolation. You have a settings page.
Multi-Tenant Architecture Choices
Separate what changes per customer from what stays shared, and most tenancy decisions become obvious. Tenant configuration, consent rules and data mappings differ by customer. Application services and core models don't.
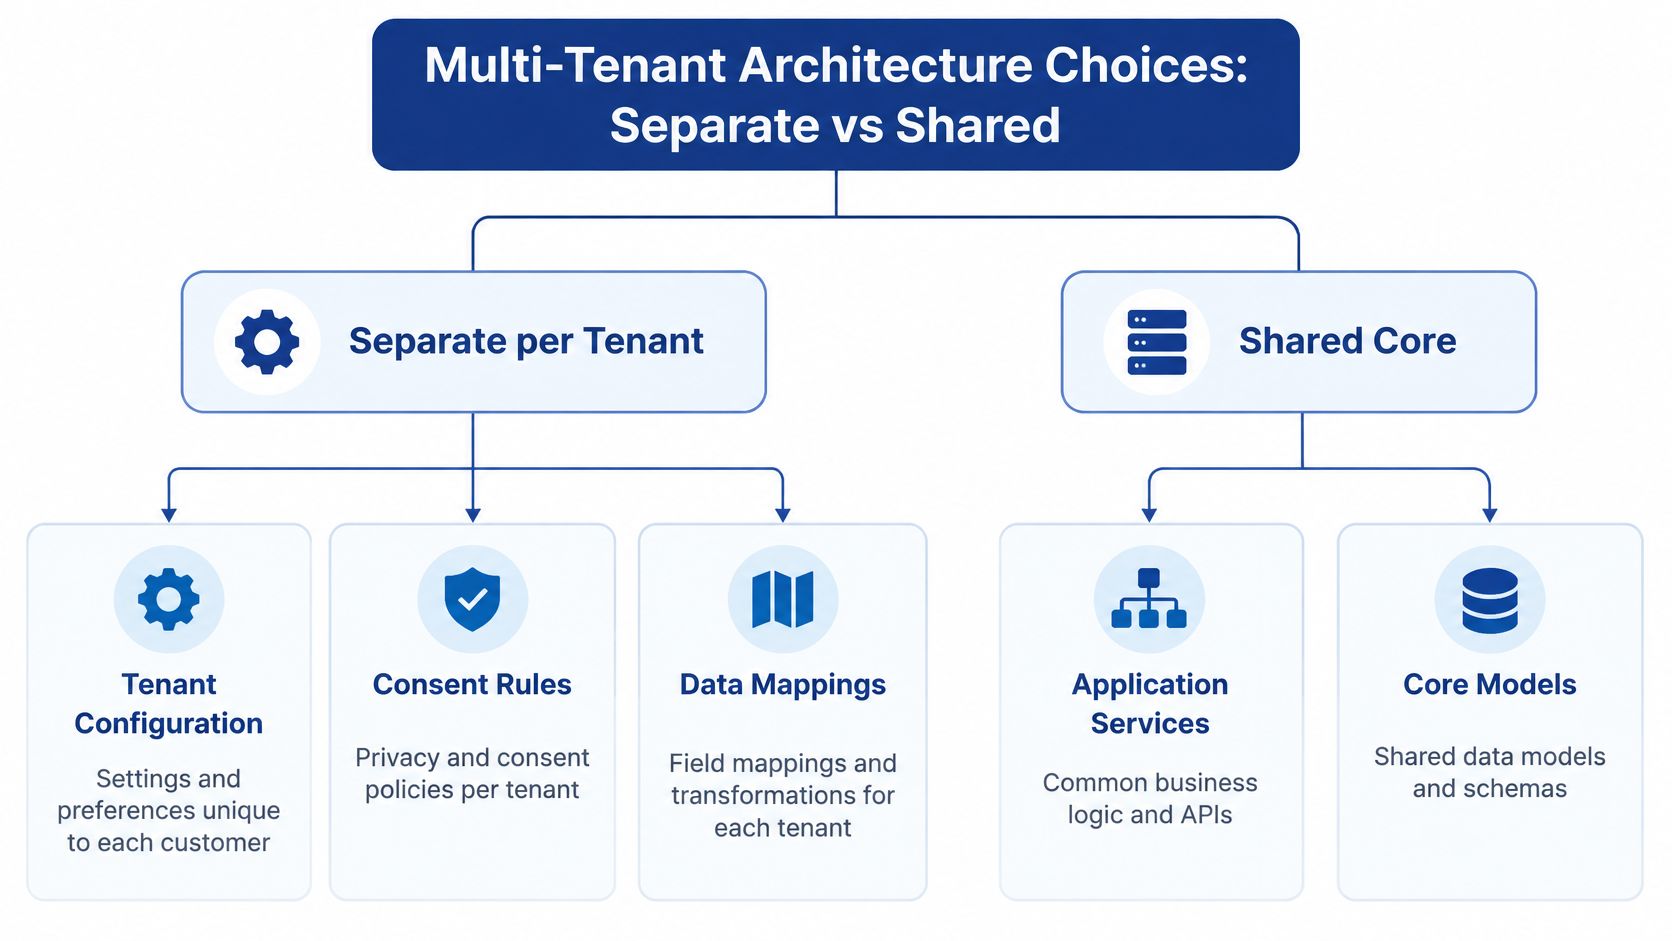
That split is the mental model to hold before comparing deployment models.
| Tenancy model | How tenants share resources | Best fit | Main trade-off |
|---|---|---|---|
| Shared database and schema | All tenants share tables, separated by a tenant ID | Startups and small clinics | Strict query isolation and noisy-neighbour risk |
| Shared application, separate databases | Each tenant has its own database | Clinic groups with several sites | More operations work for each tenant |
| Dedicated deployment per tenant | Each tenant runs its own stack | Hospitals with strict residency rules | Highest cost and slowest updates |
| Hybrid with regional cells | Shared core, with regional cells for data residency | Multi-province platforms | Most design effort before launch |
What each model looks like in practice
A startup serving five clinics on a shared schema keeps one codebase, one migration path and a single backup routine. It also lives with the constant risk that a badly written query at one clinic flattens performance for the rest, which is why connection-level tenant scoping matters more than developer discipline.
A clinic group with four sites usually lands on a separate database per site. A reporting job on one site then can't slow the others, and a restore for one site stays simple.
A hospital with strict residency rules tends to need its own stack. That customer will also expect a versioning plan, because the day you deploy everything at once is the day their change-control committee says no.
A multi-province platform ends up with a shared core and regional cells, so data lands where the rules require it without forking the product four ways.
Canada's record adoption shapes onboarding. Health Canada reported that 96.8% of Canadian family physicians used electronic medical records in 2024-25, ahead of the department's 95% target for March 2026, according to its 2024-2025 departmental results report. You're not digitising a paper clinic. You're joining a live record system, so early weeks go into migration, role mapping and reconciliation rather than setup wizardry.
The building blocks repeat across models: an API gateway for controlled interfaces, asynchronous queues for anything that can wait, versioned services, integration monitoring, and tenant-level feature flags so one customer can take a new capability before the rest.
Decision rule: pick the lightest model that meets the strictest residency requirement among your first three customers, then write down the migration path to a heavier one.
Interoperability and Integration Design
Here's the figure that should reset your roadmap. In 2024, 78% of Canadian health care providers reported at least one barrier to sharing patient information outside their main practice, and 50% named insufficient system integration, according to Statistics Canada.
Integration is the product risk, not a phase-two feature. A portal that reads cleanly from one EMR and fails on the next is a demo, not a platform.

Build on clinical entities, not screens
Model the domain once: Patient, Practitioner, Encounter, Observation, DiagnosticReport, Medication and Consent, mapped to a versioned set of FHIR profiles rather than proprietary JSON with an API bolted on. Include stable identifiers, provenance, timestamps and validation, and decide in advance how unknown or extension fields are handled when a northern lab sends something your schema never saw.
Match identities before you match messages
Two records for the same person will break more workflows than a failed message ever does. Match on verified identifiers, and send anything uncertain to a human review queue with the candidate records shown side by side. Never let the system auto-merge on name and date of birth alone.
Offer integration tiers
Exchange isn't universal, and pretending otherwise stalls sales. Federal targets in the Canada-Ontario bilateral agreement show the range: 35% of Ontarians with electronic access to their full health record, and 44% of family health service providers able to share patient information electronically, rising to 40% and 49% by March 2026. Structure tiers from secure document exchange and referral workflows, up to patient-facing access, up to full bidirectional exchange, and let a tenant move up as its own systems do.
Run it through a gateway with queueing, retry handling, duplicate detection, reconciliation dashboards and per-tenant capability flags. Track failed messages, processing latency, duplicate records and acknowledgement rates. For the message-level detail, our guide to healthcare interoperability with HL7 and FHIR APIs covers the contracts.
Test rule: conformance testing with synthetic data happens before any live EMR connection, without exception.
Development Lifecycle from Discovery to Launch
The phases below run in order, and each one produces something a clinic lead can read and challenge.
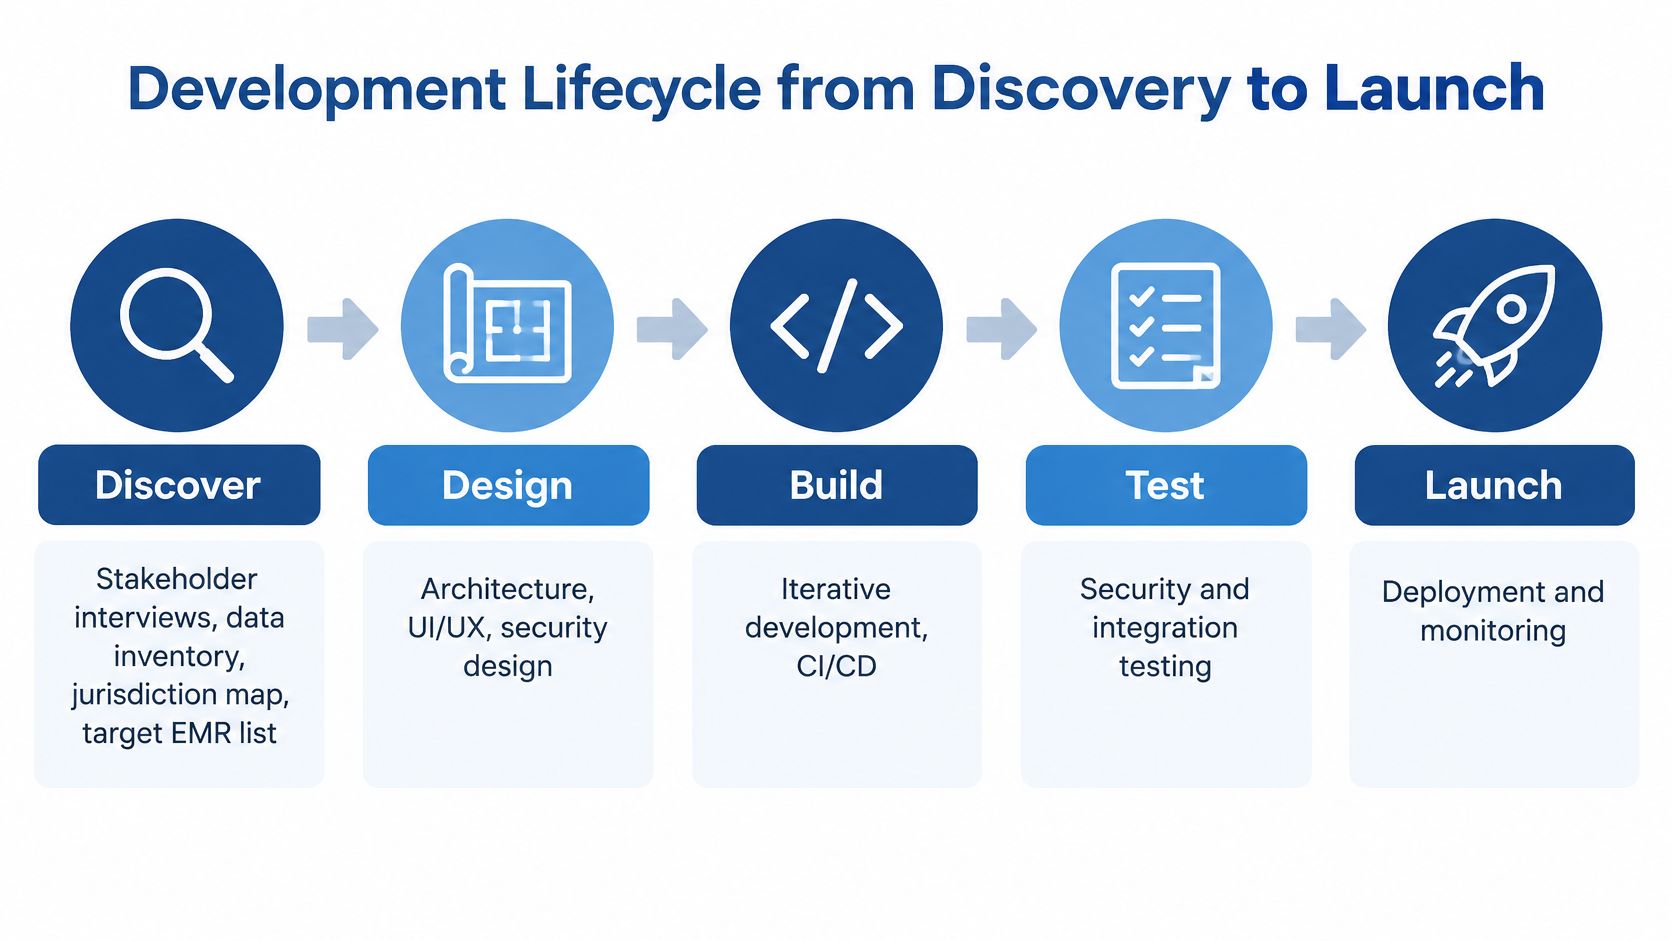
Discover: Stakeholder interviews, a data inventory, a jurisdiction map and the list of EMRs your pilot clinics run.
Design: The tenancy model, FHIR mapping, consent and purpose flows, a threat model, and a scope small enough to ship. Cleffex Digital Ltd's SaaS development process follows Discover, Design, Build and Deliver, and the design artefacts are what keep integration from turning into rework.
Build: A pilot-ready MVP, synthetic data for every integration, and automated security scans on every build.
Deliver: Conformance testing, an independent penetration test, a staged go-live with a rollback plan, and clinical sign-off on the workflows.
Support: Monitoring, incident response, version management and a fixed date for the next compliance review. We provide 24/7 maintenance and support for SaaS applications because clinical systems don't have quiet hours.
| Phase | Output to check |
|---|---|
| Discover | Stakeholder notes, data inventory, jurisdiction map, list of target EMRs |
| Design | Tenancy model, FHIR mapping, consent and purpose flows, threat model, minimum viable scope |
| Build | Pilot-ready MVP, synthetic-data tests for each integration, automated security scans |
| Deliver | Conformance results, independent penetration test, staged go-live plan with rollback, clinical sign-off |
| Support | 24/7 monitoring, incident response log, version plan, fixed compliance review schedule |
Conformance work isn't decoration. The Canadian Institute for Health Information is developing a Pan-Canadian Health Data Content Framework and Canadian Core Data for Interoperability, and its implementation guidance puts conformance testing, terminology mapping and event design before analytics or AI features. That order exists because the reverse one produces a normalisation bill that grows with every customer.
Be honest about time. A first pilot usually takes months rather than weeks, and integration is almost always the longest phase, because the external system's release schedule isn't yours to set. The question to ask at the end of each phase is simple: could you put this output in front of a clinic lead and get a clear yes or no?
Scope Your First HealthTech SaaS Release
Four questions, one page, finished this week.
Which use case ships?
Name the row from the first table. One row.
Which provinces hold the data?
This decides your storage layout and consent model, so answer it before architecture diagrams.
Which integration tier does the pilot need?
Secure document exchange is a legitimate first release. Full bidirectional exchange usually isn't.
Which tenancy model fits the strictest customer?
The strictest one, not the average one.
A development partner can carry Discover and Design while your team stays on the clinical problem. Cleffex provides healthcare software integration for North American healthtech companies, covering hospital connectivity, compliance, AI diagnostics and scalable platforms, and builds software for regulated healthcare systems and workflows. You can review that work on the healthcare software integration services page and see the wider range of software development services we offer.
Judge any partner on evidence you'd demand from your own team: a data inventory, a written tenancy decision record, and a synthetic-data integration plan. If the pilot doubles as your MVP, the healthtech MVP development guide shows how to keep that scope from creeping.
How long does a first pilot usually take?
Months, not weeks, with integration as the longest phase, as the lifecycle section sets out. Plan the go-live around the external system's schedule rather than your own.
Does a small clinic need full EMR integration on day one?
No. A secure document exchange or referral workflow earns trust first, and the integration tiers in the previous section show how a clinic moves up when its own systems are ready.
What should a development partner show after the Discover phase?
A data inventory, a jurisdiction map and a list of target EMRs, all specific enough for a clinic lead to correct. Anything vaguer means the phase isn't finished.
Cleffex Digital Ltd builds multi-tenant healthcare SaaS platforms for clinics, hospitals, insurers and healthtech startups, from the first data inventory through integration, staged launch and ongoing support. Our teams work inside the constraints this guide describes every day: provincial privacy rules, tenant isolation, and EMR connectivity that has to survive a real clinic morning. If you're planning a first release in Canada, visit Cleffex Digital Ltd, and we'll work through Discover and Design with you, with the tenancy, consent and interoperability decisions written down before the first line of code.







